PRO
CLINICAL KNOWLEDGE MAGAZINE
7 min read
Iron Deficiency – How to Avoid It

Sophia Williams
✓
Diets Premium Medical Expert • 25.09.2026
✓
Scientifically reviewed by a clinical dietitian:
This article has been peer-reviewed for adherence to IŻŻ, WHO, and PTGiP clinical nutritional standards.
| CLINICAL KNOWLEDGE MAGAZINE CLINICAL KNOWLEDGE MAGAZINE | min read 7 min |
| Diets Premium Medical Expert Sophia Williams | Scientifically reviewed by a clinical dietitian 25.09.2026 |

Smart Voice
•Listen to the article content live
0:00
/
0:00
Key Takeaways
Iron is a crucial component required for the proper functioning of our body, and its deficiency occurs quite frequently when compared to deficiencies in other essential minerals. Importantly, inadequate amounts of this microelement in the diet can lead to serious health consequences, such as a decrease in hemoglobin levels and the development of iron deficiency anemia.
Meal Plan
Want to apply these guidelines in your daily diet?
Our smart diet generator creates a tailored meal plan in 3 minutes based on the recommendations in this article.
PRO Content
PRO
This article is professional premium content (PRO) provided in its entirety.
The physiological role and multifaceted functions of iron in the human body
Iron represents an indispensable trace element that plays a pivotal role in numerous biochemical processes occurring within the human body. As a fundamental constituent of hemoglobin, it facilitates the transport of oxygen from the lungs to all tissues while also participating in the storage of this gas in muscle myoglobin. Furthermore, it is essential for erythropoiesis—the process of red blood cell production—and contributes to DNA replication and repair through the activation of specific enzymes. Its significance extends to the modulation of immune responses, supporting defensive mechanisms against bacterial and viral pathogens. Iron is a component of various enzymes that catalyze metabolic reactions, including those involved in cholesterol metabolism and the detoxification of xenobiotics in the liver. Within the body, iron exists both in functional forms—such as hemoglobin, myoglobin, tissue enzymes, and transferrin—and in storage forms, represented by ferritin and hemosiderin, which serve as a reserve of this element for periods of increased demand.
Optimal dietary iron requirements and primary food sources for human consumption
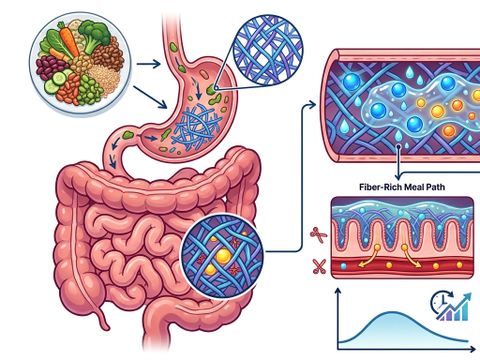
The body’s requirement for iron exhibits substantial variability depending on sex, developmental stage, and physiological condition—with adult daily needs ranging from 10 to 27 milligrams. The necessity for its consistent replenishment arises from the imperative to support rapid tissue growth, expansion of blood volume, and hemoglobin synthesis, as well as to compensate for losses such as those incurred during menstrual bleeding. Full-term newborns possess significant prenatal iron reserves; however, beginning at six months of age, dietary provision becomes essential. Consequently, the introduction of iron-rich foods is critical from the earliest stages of complementary feeding. Another pivotal period is adolescence: in girls, increased demand correlates with the onset of menstruation, whereas in boys, it aligns with elevated hemoglobin production. During pregnancy, heightened intake requirements stem from fetal development, placental formation, and the physiological rise in hemoglobin concentration. Regular hematological monitoring is essential in this phase due to the high prevalence of iron deficiency (affecting up to 40% of pregnant individuals), which may progress to anemia. For lactating women, requirements may temporarily decrease owing to the physiological absence of menstruation postpartum—typically lasting around six months, though this varies individually. Upon resumption of the menstrual cycle, demand increases once more. Primary dietary sources include meat (particularly organ meats such as liver), nuts, seeds, wheat bran, cocoa, eggs, legumes, and parsley. Contrary to popular belief, spinach contains only modest amounts of iron with poor bioavailability. In foods, this micronutrient exists in two principal forms: heme iron (highly bioavailable, found in animal products) and non-heme iron (present in plant-based foods). Its absorption efficiency is significantly influenced by other dietary components: polyphenols (in coffee, tea, red wine), phytic acid (in whole-grain products), phosphates (in cola beverages), tannins (in tea and yerba mate), and excessive fiber intake all inhibit uptake. Additionally, minerals such as calcium, manganese, and zinc may competitively impair iron absorption, a factor to consider during supplementation. Reduced absorption is also observed during diarrheal episodes and in cases of iron overload within the body.
Insufficient iron levels in the human body: etiologies, clinical manifestations, and health implications
Iron deficiency represents the most prevalent micronutrient insufficiency globally, affecting a substantial proportion of the population across diverse geographic regions. Epidemiological evidence indicates that within European nations, this condition impacts roughly 10% of women and 4% of men, whereas in low-resource settings, the prevalence may escalate to as high as 70% of the population (as documented by Korzeniowska, Wietlicka, and Jabłecka in their 2012 study). Pregnant women constitute a particularly vulnerable demographic, as their physiological iron requirements increase substantially due to fetal development and expanded maternal blood volume. The primary etiologic factors contributing to iron deficiency include: inadequate dietary intake (observed in poorly balanced vegetarian or vegan diets, general malnutrition, or eating disorders such as anorexia nervosa), elevated physiological demand (seen in pregnant women, infants, rapidly growing children, adolescents during puberty, and frequent blood donors), impaired absorption (resulting from gastric resection, chronic diarrhea, malabsorption syndromes, peptic ulcer disease, or undiagnosed celiac disease), and excessive iron loss (stemming from gastrointestinal bleeding associated with ulcers, esophageal varices, malignancies, or inflammatory conditions, as well as from heavy menstrual bleeding or other hemorrhagic sources).
Key diagnostic indicators for evaluating iron metabolism in the human body
The assessment of iron nutritional status in the human body relies on a series of specialized laboratory tests whose results facilitate a comprehensive evaluation of iron metabolism. The most critical parameters include: serum iron concentration—a commonly measured yet diagnostically limited marker due to its susceptibility to dietary fluctuations and circadian variations; ferritin levels—a reliable indicator of iron stores, though its interpretation may be confounded by inflammatory or infectious conditions; transferrin concentration—a transport protein whose synthesis increases in response to iron deficiency; transferrin saturation—a dynamic parameter influenced by the time of day; total iron-binding capacity (TIBC)—reflecting the maximum amount of iron that transferrin can bind; unsaturated iron-binding capacity (UIBC)—the difference between TIBC and current iron levels; hemoglobin (Hb) concentration—a nonspecific but valuable parameter for monitoring treatment efficacy; and mean corpuscular volume (MCV)—which only alters in advanced stages of deficiency. A holistic analysis of these indicators, frequently supplemented by a complete blood count, enables clinicians to establish an accurate diagnosis and implement an optimal supplementation or therapeutic regimen.
Iron-deficiency anemia: classification, symptomatic manifestations, and etiologic foundations of the hematologic disorder
Anemia represents a pathological condition in which hemoglobin (Hb) concentration, hematocrit (Ht) levels, and red blood cell (RBC) counts fall below established reference ranges. Based on hemoglobin levels, four distinct severity grades are recognized: **Grade I** (mild anemia) corresponds to hemoglobin values between 10 and 12 grams per deciliter; **Grade II** (moderate anemia) is defined by concentrations of 8.0–9.9 g/dL; **Grade III** (severe anemia) occurs at levels of 6.5–7.9 g/dL; and **Grade IV** (life-threatening anemia) is diagnosed when hemoglobin drops below 6.5 g/dL.
The clinical presentation typically includes pallor of the skin, persistent fatigue, muscle weakness, recurrent headaches and dizziness, impaired concentration, brittle hair and nails, heightened physical exhaustibility, and increased susceptibility to infections. It is critical to emphasize that iron deficiency is not the sole etiologic factor in anemia. The condition may also arise from deficiencies in vitamin B12 or folic acid (with particular attention to potential mutations in the *MTHFR* gene) and frequently accompanies chronic diseases, including bacterial and parasitic infections, malignant neoplasms, and autoimmune disorders. For this reason, comprehensive laboratory diagnostics and differential analysis are of paramount importance.
Targeted micronutrient supplementation for iron deficiency correction
In cases where laboratory confirmation reveals iron deficiency or iron-deficiency anemia, systematic supplementation of this trace element becomes medically indicated. With proper gastrointestinal absorption, initial improvements in biochemical markers may be detectable within seven days of commencement. However, complete restoration of the body's iron stores requires a substantially longer duration—clinical guidelines suggest that sustained normalization of parameters typically occurs only after approximately three months of uninterrupted supplementation. During this period, strict adherence to dosing schedules and implementation of a diet that enhances iron bioavailability are of paramount importance.
Sophia Williams
Diets Premium Medical Expert
Member of the Diets Premium clinical editorial board. Specializes in medical diet therapy, metabolic health, and nutritional planning.
View Profile →